The French Paradox, Lifestyle, and the Forgotten Art of Living Well

For decades, many Americans have heard about the so-called “French Paradox.” The basic observation is simple: despite consuming foods traditionally viewed as rich in fats, such as cheese, butter, and wine, the French have historically demonstrated lower rates of cardiovascular disease and obesity than Americans (Powell et al., 2010). Yet perhaps the real paradox is not found in French food itself, but in the broader cultural relationship with food, movement, stress, and daily living.

From a holistic health perspective, this discussion reveals an important truth: health is rarely the result of a single nutrient, supplement, pharmaceutical intervention, or isolated behavior. Instead, long-term wellbeing emerges from the interaction of lifestyle, environment, mindset, movement, social behavior, stress regulation, genetics, access to healthcare, and thousands of daily habits.

The modern American mindset often seeks isolated solutions to complex health problems. One week fat is considered the enemy. The next week carbohydrates become the villain. Coffee is good, but only in moderation, and now some experts suggest that as many as five cups per day may provide certain health benefits for some people (Castro, 2026). Then sugar, gluten, seed oils, cholesterol, or red meat takes center stage.

Yet the body does not function in isolated compartments. Human physiology reflects an interconnected system of behaviors, emotions, habits, environmental influences, and biological responses. The French Paradox highlights this reality.

Researchers examining lifestyle differences between France and the United States have noted several behavioral patterns among the French population. Compared with Americans, French citizens have traditionally walked more frequently, consumed more water, eaten more fresh fruits and vegetables, consumed fewer sweetened beverages, and engaged in more mindful eating behaviors (Powell et al., 2010). Meals were often smaller, slower, and more socially integrated rather than rushed and distracted. This distinction is significant.
Seeing the French Paradox Firsthand

During my recent visit to France, particularly while spending time in Paris, I was able to observe many of the lifestyle factors commonly used to explain the French Paradox. These were no longer simply ideas presented in a study, travel program, or cultural comparison. I could see many of them firsthand.

People walked almost everywhere. They walked through neighborhoods, along the Seine, between shops, to cafés, to Metro stations, and through long corridors connecting public transportation systems. They routinely climbed stairs, carried groceries, stood while waiting for trains, and incorporated physical activity into the normal activities of daily life.

I also noticed what appeared to be fewer overweight individuals and considerably fewer people with morbid obesity than I commonly observe in many parts of the United States. This was only my personal observation and not a controlled scientific assessment. Nevertheless, people across a range of ages seemed, on average, leaner, more mobile, and more physically functional.

Older adults were frequently walking through the city, using public transportation, shopping, and navigating stairs without the same degree of visible physical limitation that I often see elsewhere. Many people appeared to maintain a level of practical fitness, not necessarily because they attended gyms or followed highly structured exercise programs, but because movement remained integrated into the architecture and rhythm of everyday life.

The environment itself encouraged activity. Compact neighborhoods, public transportation, smaller shops, pedestrian areas, and limited dependence on automobiles made walking a necessity rather than merely an optional form of exercise. It became increasingly clear to me that the design of a community can either support health or quietly discourage it.

The eating culture also appeared different. People often sat at cafés and restaurants rather than eating hurriedly in their cars. Meals appeared to be social occasions and opportunities for conversation. Portions often seemed more moderate, and there appeared to be greater emphasis on the experience and quality of food rather than simply consuming as much as possible, as quickly as possible.

These observations seemed to support many of the lifestyle explanations commonly associated with the French Paradox. However, another highly visible behavior complicated the picture. Smoking tobacco and vaping appeared to be widespread among people of many ages and demographics. I saw young adults, middle-aged individuals, older adults, men, and women smoking cigarettes or using vaping devices outside cafés, on sidewalks, near public buildings, and while socializing. The irony was difficult to overlook.

On one hand, many people appeared leaner, more active, and more physically capable. On the other hand, tobacco and nicotine use were openly integrated into everyday life. This serves as an important reminder that appearing thin or fit does not automatically mean that someone is healthy. Body size is only one outward indicator, and it cannot reveal lung function, vascular damage, blood pressure, cholesterol, cancer risk, emotional wellbeing, or the cumulative effects of nicotine exposure.

A culture may perform well in one dimension of health while struggling in another. The French may benefit from greater daily movement, smaller portions, and stronger social rituals surrounding food, while simultaneously carrying substantial health risks related to smoking, alcohol consumption, hypertension, and other cardiovascular factors.

This is precisely why holistic health requires a broader view.

The American Contrast

In the United States, eating often occurs while driving, working, watching television, scrolling through social media, or functioning under psychological stress. Meals are frequently consumed rapidly and in excessive portions.

Ultra-processed foods dominate much of the modern dietary landscape, contributing to excessive intake of sodium, refined sugars, additives, preservatives, and industrially formulated fats. Many of these products are specifically engineered for convenience and hyper-palatability rather than nourishment, making it easier to consume large quantities before the body’s natural satiety signals have time to respond (Monteiro et al., 2019).

Holistically speaking, this creates more than a nutritional problem. It also creates metabolic, behavioral, emotional, and nervous system problems.

The human organism does not function optimally while chronically stressed, overstimulated, sleep deprived, sedentary, emotionally dysregulated, and disconnected from natural rhythms. Traditional Eastern systems such as Traditional Chinese Medicine and Ayurveda have long emphasized that digestion is influenced by emotional balance, stress, circulation, breathing, rest, and lifestyle behaviors.

Modern research increasingly examines similar relationships through the study of inflammation, autonomic nervous system regulation, metabolic syndrome, the microbiome, and the gut-brain axis (Mayer, 2016).

Interestingly, the traditional French approach to eating appears to support the parasympathetic, or “rest and digest,” side of the nervous system. Meals are often approached as experiences rather than fuel-loading events. Walking remains incorporated into daily life. Social connection around meals is common. Portion control may be supported through pacing and satiety awareness rather than calorie obsession.

This does not mean that French culture is perfect, nor does it mean that red wine is a magical health tonic. Researchers have cautioned against oversimplifying the paradox and attributing it to wine or any other single factor (Law & Wald, 1999).

Health outcomes are more likely to arise from multiple interacting lifestyle, cultural, medical, economic, and environmental variables.

Is the French Paradox Partly a Statistical Paradox?

Although the French Paradox remains an interesting and useful concept, it should not be accepted without critical examination. Some researchers have questioned whether France’s historically low reported coronary heart disease mortality reflects only superior health, or whether part of the difference may be related to the ways disease and death were diagnosed, classified, and reported.

One proposed source of bias is the under-certification of coronary heart disease on French death certificates. A death influenced by coronary disease might sometimes have been attributed to heart failure, an unspecified circulatory condition, sudden death, or another immediate complication rather than to the underlying coronary disease itself.

Law and Wald (1999) examined this possibility and concluded that differences in death certification could explain a meaningful portion of the apparent mortality difference between France and countries such as Britain, although they did not suggest that reporting differences explained the entire phenomenon.

Other researchers have reached a similar conclusion. Ferrières (2004) acknowledged that French physicians may have under-certified some coronary deaths. However, after researchers examined standardized data from the World Health Organization’s MONICA project, France still demonstrated comparatively low coronary attack and mortality rates. Therefore, underreporting appears to be a possible bias, but probably not a complete explanation for the French Paradox (Ferrières, 2003).

This distinction is important. It would be inaccurate to say that the French Paradox is entirely a statistical illusion. At the same time, it would also be unwise to assume that mortality figures from different countries are perfectly comparable.

Death certificates are completed by individual physicians, and the accuracy of the final classification depends on available medical information, diagnostic practices, terminology, coding systems, and the physician’s judgment. French research comparing electronic and paper death certification found that electronic certificates included more reported causes and were considerably less likely to contain imprecise information, demonstrating that even the method used to record a death can affect the quality of national statistics (Lefeuvre et al., 2013).

Therefore, the more accurate statement may be that France historically had lower recorded coronary mortality, but some portion of the difference could have resulted from how coronary deaths were documented and categorized.

Underdiagnosis Is Not the Same as Good Health

Mortality statistics present only one part of the picture. People may live for many years with hypertension, diabetes, high cholesterol, vascular disease, or early-stage coronary disease without knowing that they have these conditions.

Recent reporting from Santé publique France found that awareness of major metabolic risk factors remains surprisingly low. Among French adults affected by these conditions, approximately 23% of those with diabetes and as many as 45% of those with hypertension were unaware that they had the condition (Olié et al., 2025).

This means that health problems do not necessarily have to be intentionally concealed or deliberately unreported to remain absent from national surveys. Many people simply do not know that they have them.

A person may appear thin, walk daily, and function well while still having elevated blood pressure, high LDL cholesterol, insulin resistance, or developing atherosclerosis. Conversely, an overweight individual may be actively improving their diet, exercising, sleeping well, and receiving appropriate preventive care.

Visible body composition provides useful information, but it never tells the whole story.

Current data also show that cardiovascular disease remains the second-leading cause of death in France, while hypertension, obesity, diabetes, and elevated LDL cholesterol continue to represent substantial public health concerns. France is healthier than some countries according to certain measures, but it is not immune to the chronic diseases affecting other industrialized nations. (“Assessment of the Quality of Death Certificates in France: The Role of Electronic Certification,” 2013)

The World Health Organization also notes that France now has relatively complete and high-quality cause-of-death registration. This suggests that historical reporting bias should be considered without assuming that modern French health statistics are generally unreliable (“France,” n.d.).

The Limits of Population-Level Comparisons

Another weakness in many explanations of the French Paradox is that they rely on broad national averages. Researchers may compare average saturated-fat consumption, average wine consumption, and national coronary mortality, but these figures do not prove that the individuals eating the most saturated fat or drinking the most wine are the same individuals avoiding heart disease.

This is sometimes called an ecological limitation or ecological fallacy.

Population-level associations cannot establish individual cause and effect. They may also overlook differences in food quality, meal timing, total caloric intake, socioeconomic status, healthcare access, stress, genetics, physical activity, smoking, and the types of fats being consumed (Ferrières, 2004).

Even the phrase “the French diet” may be misleading. France contains different regions, socioeconomic groups, cultural traditions, occupational patterns, and levels of access to quality food and healthcare. A physically active Parisian who shops daily and walks to public transportation may live very differently from someone in a more car-dependent or economically disadvantaged area.

Similarly, there is no single American lifestyle. The habits of an active individual who eats whole foods and regularly engages with a supportive community should not be equated with those of someone who is isolated, sedentary, sleep deprived, and dependent on ultra-processed food.

National labels can help us identify broad patterns, but they can also hide important differences between individuals.

The Time-Lag Explanation

Law and Wald (1999) offered another challenge to simplistic interpretations of the French Paradox. They suggested that coronary mortality often reflects dietary patterns from decades earlier rather than only what a population is eating today.

A population may increase its intake of saturated fat, processed food, or total calories, but the full cardiovascular consequences may not become visible for many years. France’s historically lower coronary mortality may therefore have reflected earlier dietary and lifestyle conditions rather than complete protection from more recent habits.

This time-lag explanation reminds us that chronic disease develops gradually. Atherosclerosis, insulin resistance, loss of mobility, and metabolic dysfunction may progress quietly for years before producing obvious symptoms or a medical crisis.

The consequences of today’s collective habits may not be fully visible until years or even decades from now.

Learning Without Romanticizing

The purpose of examining the French Paradox should not be to romanticize France, condemn America, or suggest that one culture has solved the health equation.

Every culture contains both strengths and contradictions.

France may offer valuable lessons about walking, portion awareness, food quality, social meals, public transportation, and integrating movement into everyday life. At the same time, the prevalence of smoking and vaping that I witnessed firsthand demonstrates how a visibly active population can continue to normalize behaviors that undermine cardiovascular, respiratory, and long-term systemic health.

The United States has reduced cigarette smoking considerably over recent decades, yet it continues to struggle with obesity, sedentary living, chronic stress, sleep disruption, social isolation, and the widespread consumption of ultra-processed food.

One country’s strengths may expose another country’s weaknesses, but its weaknesses should also prevent us from treating it as an ideal.

A holistic perspective asks a better question: Which cultural patterns support human wellbeing, which patterns undermine it, and what can we thoughtfully learn from both?

The Body Responds to Patterns

Health cannot be fully outsourced to pharmaceuticals, wearable technology, supplements, or calorie-tracking applications while fundamental lifestyle dysfunction remains unaddressed.

One cannot chronically overeat ultra-processed foods, avoid movement, live under constant stress, sleep poorly, and expect long-term wellness simply by taking medications or vitamins. At the same time, one should not assume that walking frequently or maintaining a lower body weight will erase the harms associated with smoking, excessive alcohol consumption, poor sleep, or untreated hypertension.

The body responds to patterns. Walking daily, breathing deeply, social connections, preparing meals, eating slowly, time in nature, adequate sleep, emotional regulation, and stress management are all factors that determine wellness. Avoiding tobacco matters. Receiving appropriate preventive screening and medical care also matters.

Human beings evolved within rhythms of movement, sunlight, labor, recovery, and community, not endless stimulation, convenience foods, digital overload, and physical inactivity.

The French Paradox may therefore be less about French cuisine and more about the complex consequences of lifestyle patterns within modern industrial cultures. Some of these patterns may protect health, some may undermine it, and others may take decades to reveal their full effects.

The Warrior, Scholar, and Sage

From the perspective of the Warrior, Scholar, and Sage framework, true wellness requires balance among physical discipline, intellectual awareness, and emotional and spiritual regulation.

The Warrior cultivates movement, resilience, strength, and physical vitality.

The Scholar develops knowledge and discernment regarding nutrition, research, statistics, behavior, and culture. The Scholar also recognizes that an attractive theory should not be accepted uncritically simply because it confirms what we would like to believe.

The Sage practices moderation, mindfulness, gratitude, and intentional living. The Sage understands that no country, culture, diet, or healthcare system possesses all the answers.

Ultimately, holistic wellbeing is not built upon isolated hacks, miracle foods, romanticized lifestyles, or national stereotypes. It is cultivated through daily patterns that support harmony among the body, mind, behavior, environment, and community.

My recent visit to France allowed me to see many of the factors commonly associated with the French Paradox firsthand. I saw more daily walking, apparently lower levels of severe obesity, active older adults, smaller portions, social meals, and communities designed around human movement.

I also saw widespread smoking and vaping, reminding me that wellbeing cannot be determined solely by appearance, body weight, or one favorable set of statistics.

Perhaps the greatest lesson hidden within the French Paradox is not that the French have discovered a secret that allows them to consume rich foods without consequences. Perhaps it is that health is complex, statistics require interpretation, cultures contain contradictions, and wellbeing is not merely about what we eat.

It is about how we live.

References

Assessment of the quality of death certificates in France: The role of Electronic certification. (2013, March 5). Retrieved from https://www.santepubliquefrance.fr/en/docs/article/assessment-quality-death-certificates-france-role-electronic-certification?utm_source=chatgpt.com

Castro, A. (2026, July 20). Scientists reveal why up to 5 cups of coffee a day may benefit heart health. Newsweek.

Ferrières, J. (2004). The French paradox: Lessons for other countries. Heart, 90(1), 107–111. https://doi.org/10.1136/heart.90.1.107

France. (n.d.). Retrieved from https://data.who.int/countries/250

Law, M., & Wald, N. (1999). Why heart disease mortality is low in France: The time lag explanation. BMJ, 318(7196), 1471–1480. https://doi.org/10.1136/bmj.318.7196.1471

Lefeuvre, D., Pavillon, G., Aouba, A., Lamarche-Vadel, A., Fouillet, A., Jougla, E., & Rey, G. (2013). Assessment of the quality of death certificates in France: The role of electronic certification. Bulletin Épidémiologique Hebdomadaire, (7), 57–60.

Mayer, E. A. (2016). The mind-gut connection: How the hidden conversation within our bodies impacts our mood, our choices, and our overall health. Harper Wave.

Monteiro, C. A., Cannon, G., Levy, R. B., Moubarac, J. C., Louzada, M. L. C., Rauber, F., Khandpur, N., Cediel, G., Neri, D., Martinez-Steele, E., Baraldi, L. G., & Jaime, P. C. (2019). Ultra-processed foods: What they are and how to identify them. Public Health Nutrition, 22(5), 936–941. https://doi.org/10.1017/S1368980018003762

Olié, V., Gabet, A., Grave, C., Helft, G., Fosse-Edorh, S., Piffaretti, C., Lailler, G., Verdot, C., Deschamps, V., Vay-Demouy, J., Vidal-Petiot, E., Duly-Bouhanik, B., Tuppin, P., Ferrières, J., Halimi, J. M., & Blacher, J. (2025). Epidemiology of cardiovascular risk factors: Non-behavioral risk factors. Bulletin Épidémiologique Hebdomadaire, special issue, 102–116.

Powell, L. H., Kazlauskaite, R., Shima, C., & Appelhans, B. M. (2010). Lifestyle in France and the United States: An American perspective. Journal of the American Dietetic Association, 110(6), 845–847. https://doi.org/10.1016/j.jada.2010.03.029


The Price of Things Worth Having

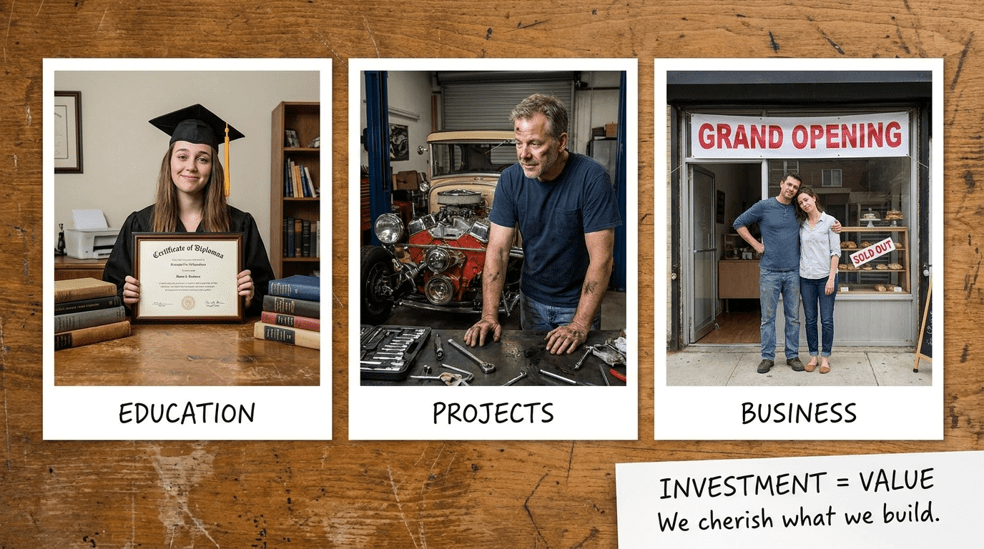
One lesson that has become increasingly clear to me over the years is that almost everything worth achieving, obtaining, or owning is ultimately temporary. Our health changes. Our wealth comes and goes. Our careers end. Our homes eventually belong to someone else. Even our accomplishments and reputations gradually fade with time. Ultimately, every one of us is merely borrowing time on this earth.

At first glance, this realization might appear discouraging. If everything is temporary, then why strive for anything at all?

I have come to the opposite conclusion.

It is precisely because life is temporary that our choices matter. Our limited time gives value to the decisions we make, the relationships we cultivate, the knowledge we pursue, and the efforts we invest. The temporary nature of life does not diminish its meaning. Rather, it enhances it.

This understanding has been expressed in many philosophical and spiritual traditions. Buddhism teaches the principle of impermanence, often referred to as anicca, recognizing that all conditioned things continually arise, change, and pass away. Taoism similarly reminds us that nature exists in constant transformation. The seasons change. Rivers continually flow. The human body is never static. Even our thoughts, emotions, successes, and disappointments are temporary visitors rather than permanent residents. The Stoics likewise encouraged reflecting upon the temporary nature of life, not to produce despair, but rather gratitude, humility, and wise action (Marcus Aurelius, ca. AD 180/2002; Epictetus, ca. AD 108/1998).

Recognizing impermanence is not an invitation to become indifferent. Rather, it encourages us to appreciate the present while remaining less attached to outcomes beyond our control.

Nearly everything of lasting significance requires some form of exchange. Whether the goal is better health, financial security, meaningful relationships, wisdom, or personal fulfillment, there is usually a price to pay. That price may involve time, physical effort, emotional energy, money, discipline, patience, sacrifice, or some combination of these resources.

There are very few meaningful rewards that simply appear without investment.

As I have often written, health is an excellent example. People frequently search for the newest supplement, miracle diet, medication, or exercise program that promises dramatic results with minimal effort. While many products and treatments certainly have their place, there remains one consistent reality. Good health cannot simply be purchased. It must continually be earned through thousands of daily decisions involving movement, nutrition, sleep, stress management, relationships, and personal responsibility.

Likewise, wisdom cannot be downloaded. Character cannot be inherited. Resilience cannot be bought. These qualities are developed gradually through experience, reflection, adversity, education, and perseverance.

Psychologists have long recognized that people often place greater value on things they have worked to obtain. One explanation is known as effort justification, where individuals perceive greater worth in outcomes that required significant effort (Festinger, 1957; Aronson & Mills, 1959). Similarly, the IKEA effect describes our tendency to value objects more highly when we have personally invested effort into creating or assembling them (Norton et al., 2011).

In other words, the investment itself often increases our appreciation.

This helps explain why many things that are freely given are sometimes underappreciated. When little or no personal investment exists, there may be less emotional attachment, less gratitude, and less commitment to maintaining what has been received.

Of course, there are important exceptions.

Many of life’s greatest blessings are not earned in the traditional sense. Loving parents, supportive friends, devoted spouses, gifted teachers, scholarships, unexpected opportunities, and even life-saving medical care may come through the generosity of others rather than through our own efforts. These gifts should never be viewed as having less value simply because they were freely given.

The difference lies in how we respond.

Even if something comes without financial cost, it still deserves appreciation, stewardship, and responsibility. Gratitude itself becomes a form of investment. We honor gifts not merely by receiving them, but by using them wisely and paying their benefits forward whenever possible.

Our modern culture often encourages the pursuit of shortcuts. We see advertisements promising rapid weight loss, instant wealth, overnight success, effortless investing, accelerated learning, and immediate happiness. Social media frequently amplifies this illusion by highlighting accomplishments while concealing the years of work, failures, sacrifices, and disappointments that preceded them.

People naturally seek the easiest path.

Psychologists describe this tendency as a preference for immediate gratification. Yet decades of research demonstrate that the ability to delay gratification is associated with numerous positive long-term outcomes, including academic achievement, financial stability, healthier lifestyles, and emotional regulation (Mischel et al., 1989; Duckworth et al., 2013).

Nature itself offers the same lesson. Trees require years to mature. Muscles strengthen only after repeated stress and recovery. Healthy relationships deepen through shared experiences. Wisdom develops through reflection upon both success and failure. There are no meaningful shortcuts around growth itself.

My own studies in martial arts, Tai Chi, Qigong, holistic wellness, and Eastern philosophy have reinforced this lesson repeatedly. Beginners often ask how long it takes to develop skill, balance, relaxation, internal awareness, or true self-mastery. While instruction can certainly accelerate learning, no teacher can breathe for another person, perform another person’s exercises, or cultivate another person’s character.

The student must ultimately make the exchange. Every practice session becomes an investment. Every hour of study becomes an investment. Every difficult decision becomes an investment. Every healthy meal, every mindful breath, every walk, every setback, and every act of discipline gradually shape the person we become.

This is where another Taoist principle has become increasingly meaningful to me. The concept of wu wei is often misunderstood as “doing nothing.” More accurately, it suggests acting in harmony with natural principles rather than struggling against them. The oak tree does not force itself to mature overnight. Rivers do not compete with mountains. They simply continue flowing, eventually carving valleys through persistent movement.

Likewise, meaningful self-development rarely occurs through frantic effort alone. It emerges through consistent, intelligent, sustainable practice repeated over months and years. The greatest transformations are often nearly invisible while they are occurring.

Ironically, because everything is temporary, perhaps the process becomes even more valuable than the outcome itself.

A beautiful home eventually ages. Financial wealth changes hands. Professional titles disappear after retirement. Physical strength gradually declines. Even our memories eventually fade.

Yet the habits, discipline, wisdom, compassion, resilience, humility, and discernment developed while pursuing these goals become woven into our character. They influence our families, our students, our communities, and often generations beyond our own lifetime. Perhaps that is the true return on investment.

Another lesson I continue learning is the distinction between appreciation and attachment. Appreciation allows us to fully enjoy the people, experiences, and possessions presently in our lives. Attachment often convinces us that our happiness depends upon permanently possessing them. The first encourages gratitude. The second often produces anxiety.

Holistic wellness extends beyond nutrition and exercise. It also includes cultivating a healthier relationship with success, failure, gain, loss, praise, criticism, youth, aging, and eventually even mortality. These are not problems to solve but realities to understand.

As I continue growing older, I find myself placing less importance on acquiring possessions and more importance on becoming a better steward of whatever time remains. My purpose has never centered upon accumulating things. Rather, it has been to help others improve their lives through education, encouragement, practical self-care, and hopefully a little greater wisdom than they possessed before we met.

Even that effort requires an exchange. Teaching requires preparation. Writing requires research. Listening requires patience. Serving requires compassion. Learning requires humility. Living well requires continual discernment. The rewards are rarely immediate, and they are seldom measured financially. Yet they often produce benefits extending far beyond anything we may personally witness.

Modern psychology, Stoic philosophy, Taoism, Buddhism, and many other wisdom traditions ultimately converge upon a remarkably similar insight. Although they use different language, they each recognize that meaning is found less in possessing and more in becoming.

Life’s greatest treasures are seldom free. They require investment, sacrifice, patience and most importantly, they require our most precious commodity, our limited time.

In the end, everything we own will eventually be left behind. Our possessions will belong to someone else. Our titles will be forgotten. Even our physical bodies will one day return to the earth. What remains is not what we accumulated. What remains is the life we lived, the character we developed, the people we influenced, and the legacy of compassion, wisdom, and integrity we leave behind.

Perhaps that is the most valuable investment any of us can ever make.

References

Aronson, E., & Mills, J. (1959). The effect of severity of initiation on liking for a group. The Journal of Abnormal and Social Psychology, 59(2), 177–181. https://doi.org/10.1037/h0047195

Duckworth, A. L., Tsukayama, E., & Kirby, T. A. (2013). Is it really Self-Control? Examining the predictive power of the delay of gratification task. Personality and Social Psychology Bulletin, 39(7), 843–855. https://doi.org/10.1177/0146167213482589

Epictetus. (1998). The enchiridion (S. Walton, Trans.). Dover Publications. (Original work published ca. AD 108) https://archive.org/details/epictetus-the-enchiridion

Festinger, L. (1957). A theory of cognitive dissonance. Stanford University Press. https://archive.org/details/theoryofcognitiv0000fest/page/n5/mode/2u

Viktor E. Frankl. (2006). Man’s search for meaning. Beacon Press. (Original work published 1946)

Laozi. (1993). Tao Te Ching (D. C. Lau, Trans.). Everyman. (Original work written ca. 4th century BCE)

Marcus Aurelius. (2002). Meditations (G. Hays, Trans.). Modern Library. (Original work written ca. AD 180) https://dn790009.ca.archive.org/0/items/meditation-GeorgeHays/meditations-GeorgeHays.pdf

Mischel, W., Shoda, Y., & Rodriguez, M. L. (1989). Delay of gratification in children. Science, 244(4907), 933–938. https://doi.org/10.1126/science.2658056

Norton, M. I., Mochon, D., & Ariely, D. (2011). The IKEA effect: When labor leads to love. Journal of Consumer Psychology, 22(3), 453–460. https://doi.org/10.1016/j.jcps.2011.08.002

Cortisol Rhythms, Bright Light, and Migraine Experiences

Dr. Andrew Huberman’s exploration of cortisol profoundly reframed its role: it is far more than a “stress hormone.” Cortisol functions as a daily energy distributor, mobilizing glucose, especially to the brain so individuals can wake up, focus, and function effectively.

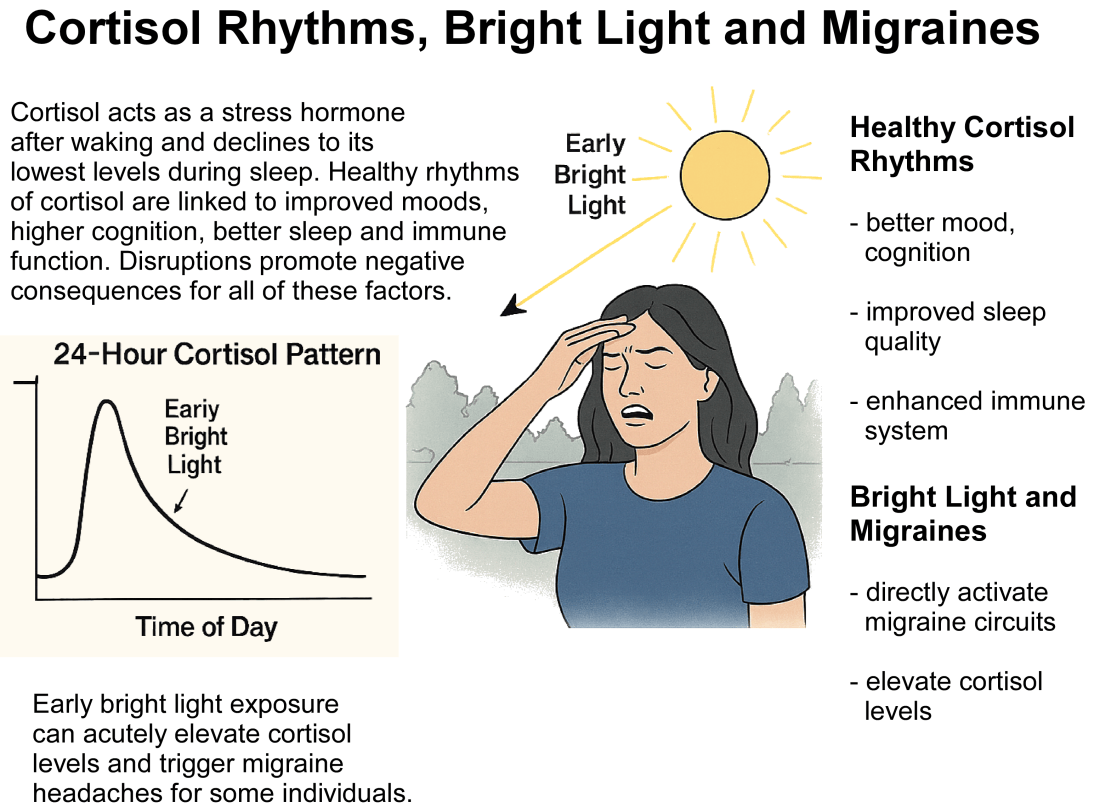
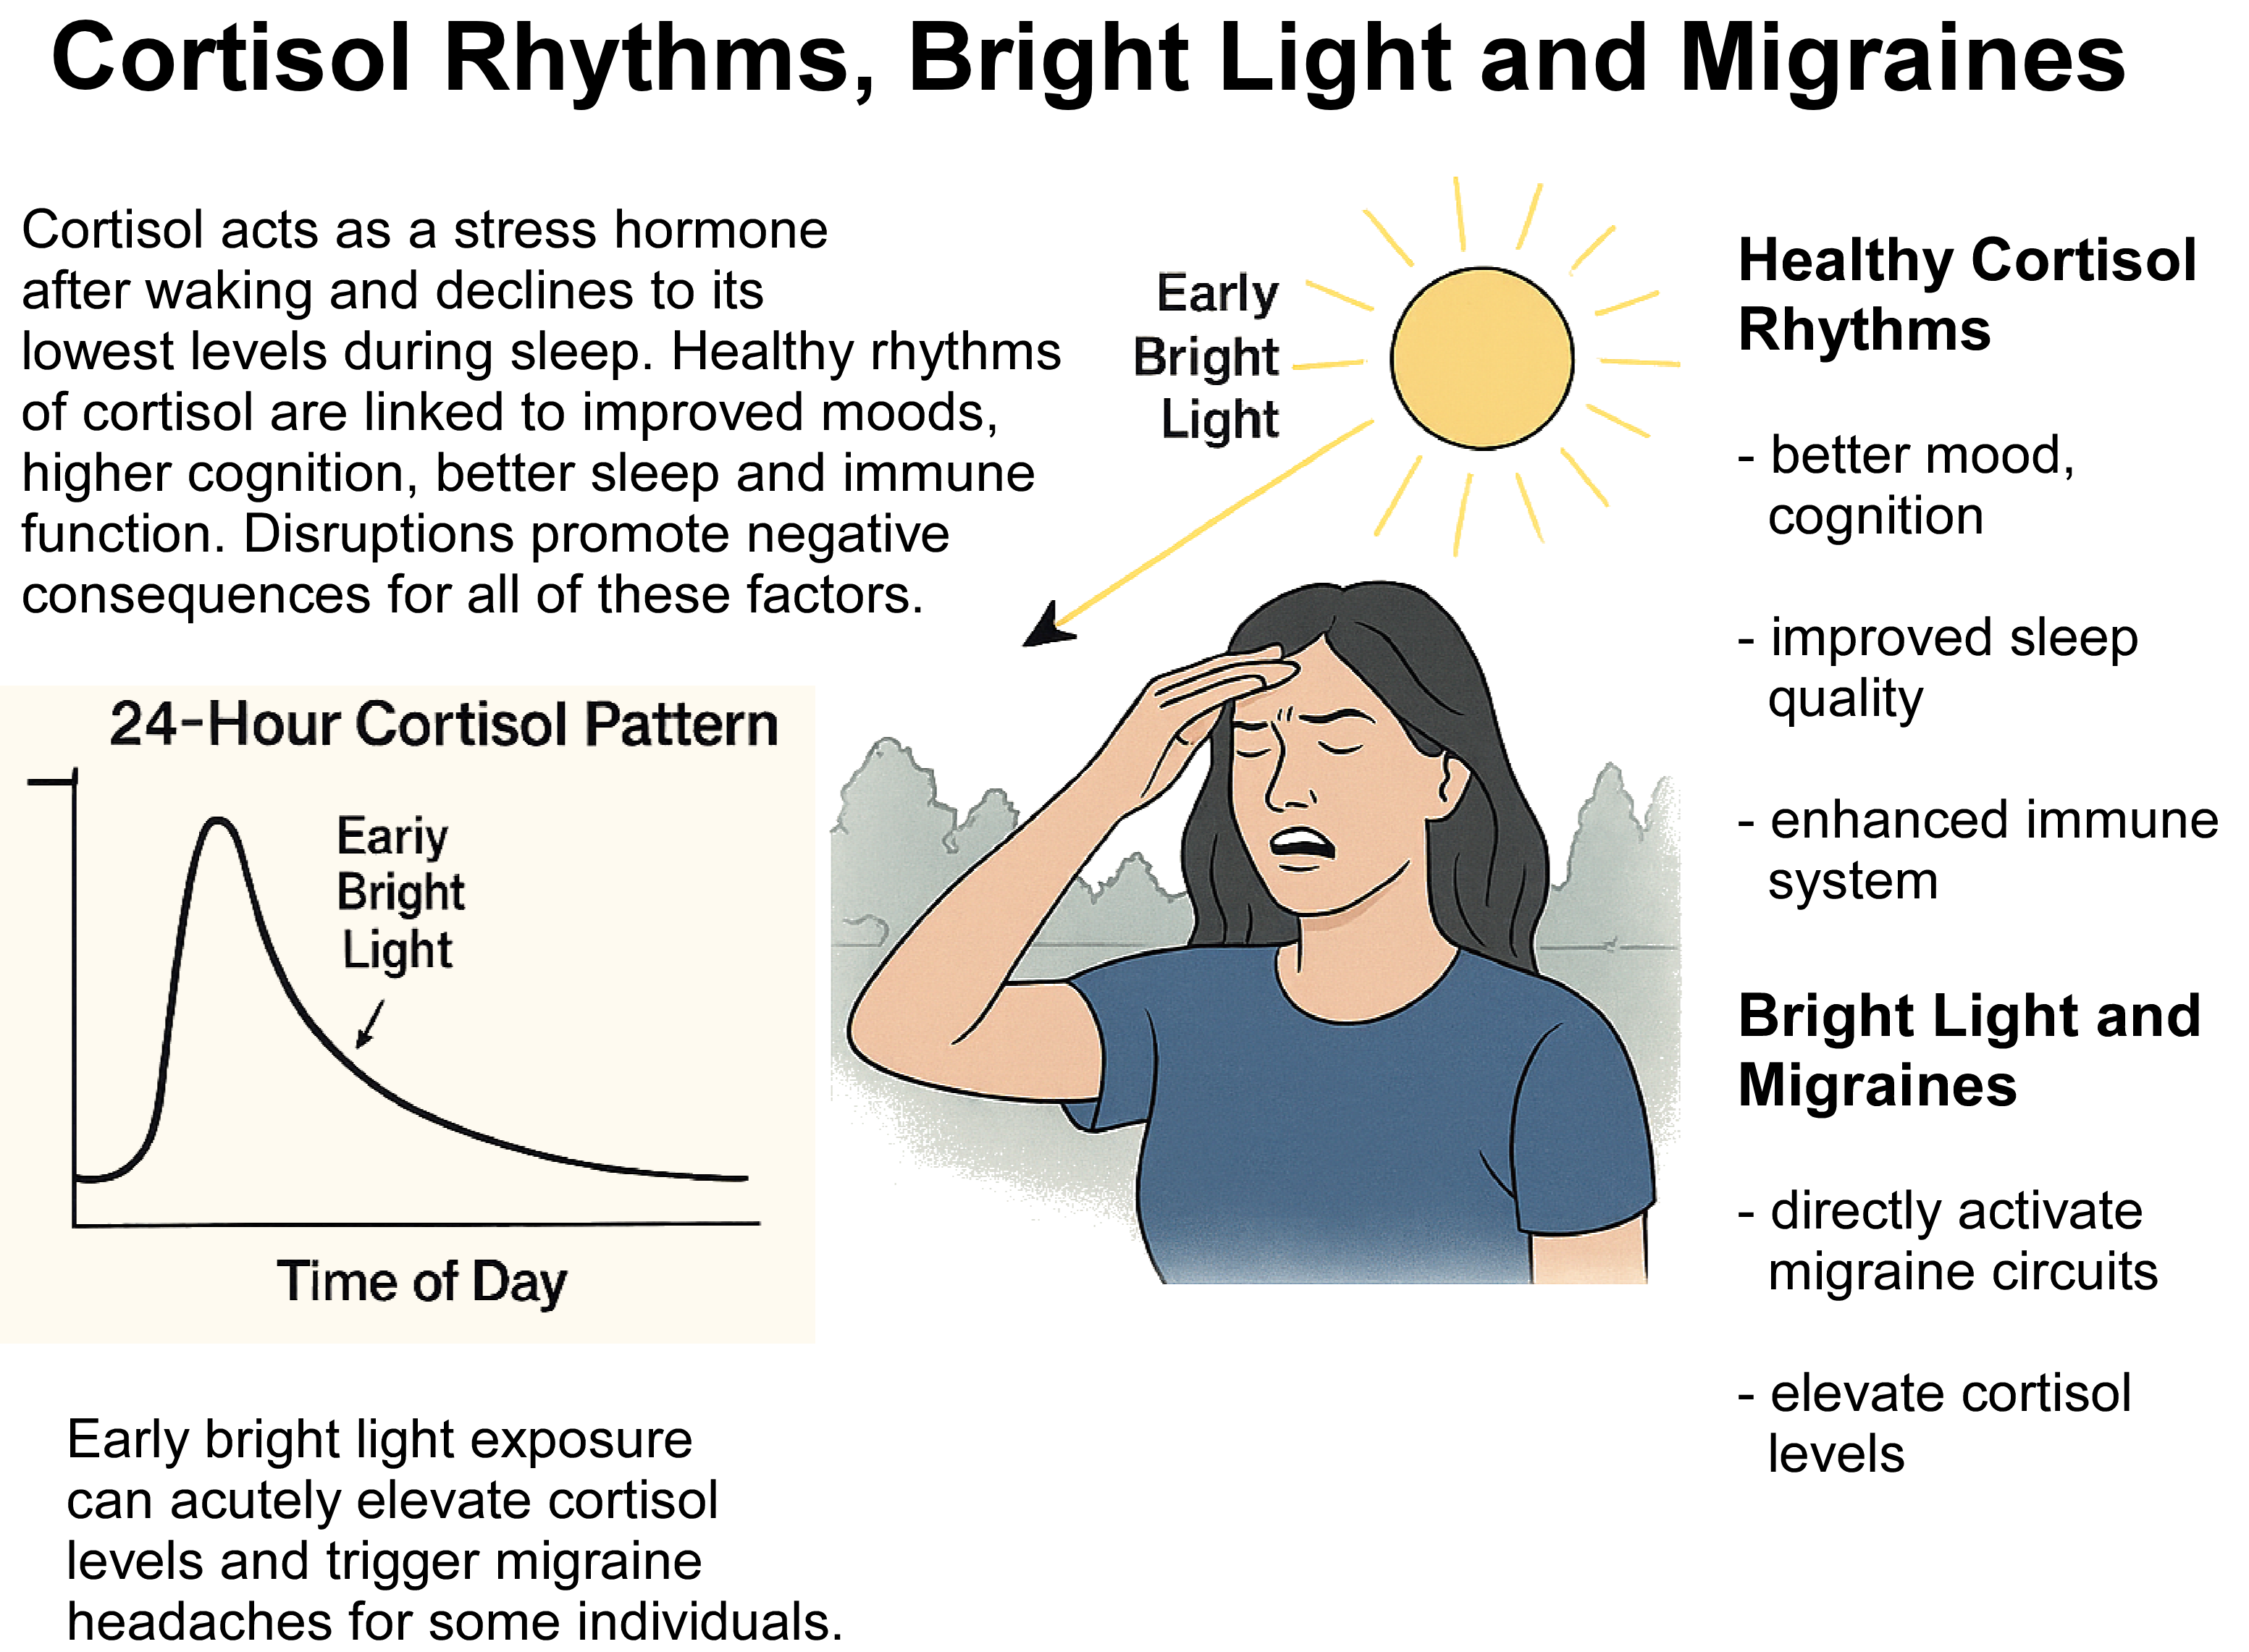
Cortisol exhibits a reliable 24-hour rhythm: following the cortisol awakening response (CAR), levels peak within 30–45 minutes of waking and subsequently decline to the lowest levels during early sleep (Fries, Dettenborn, & Kirschbaum, 2009; Rüger et al., 2006). When this rhythm remains intact, it supports resilience, mood, cognition, sleep, and immune function. Disruption via stress, poor habits, or inconsistent sleep can impair these domains (Franklyn-Miller, 2025).

Dr. Huberman describes how the HPA axis and the suprachiasmatic nucleus (SCN) collaborate to regulate cortisol. He advocates for morning light exposure (ideally natural sunlight) to boost early-day cortisol release and support circadian timing (Huberman Lab, 2025). Complementary strategies include hydration upon waking, delaying caffeine by an hour, exercising consistently, and supporting sustained energy through nutrition. Also, sometimes using agents like grapefruit or black licorice to modestly extend cortisol’s effects (with caution due to potential risks). Evening strategies include dimming lights, especially minimizing blue light, avoiding late caffeine, incorporating starchy carbohydrates at dinner, and using non-sleep deep rest (NSDR) or slow breathing to facilitate healthy cortisol decline.

Huberman also outlines burnout archetypes: those who wake wired but crash afternoon, and those sluggish in the morning but restless at night, each necessitating tailored protocols. He warns of cortisol’s long-term neurological impact: chronic mis-timed elevation can damage the hippocampus, a key structure for learning and memory, and aging or chronic illness often blunt the cortisol curve, increasing health risks and decreasing resilience (Franklyn-Miller, 2025; Huberman Lab, 2025).

Empirical Migraine Observations Connect with Cortisol and Light

Across four decades of journaling, I myself have observed that bright light exposure near the time of sunrise consistently triggered migraines. This pattern occurred regardless of hydration, caffeine, food, or sleep quality, which indicates a robust and reliable relationship between early-day light and migraine onset.

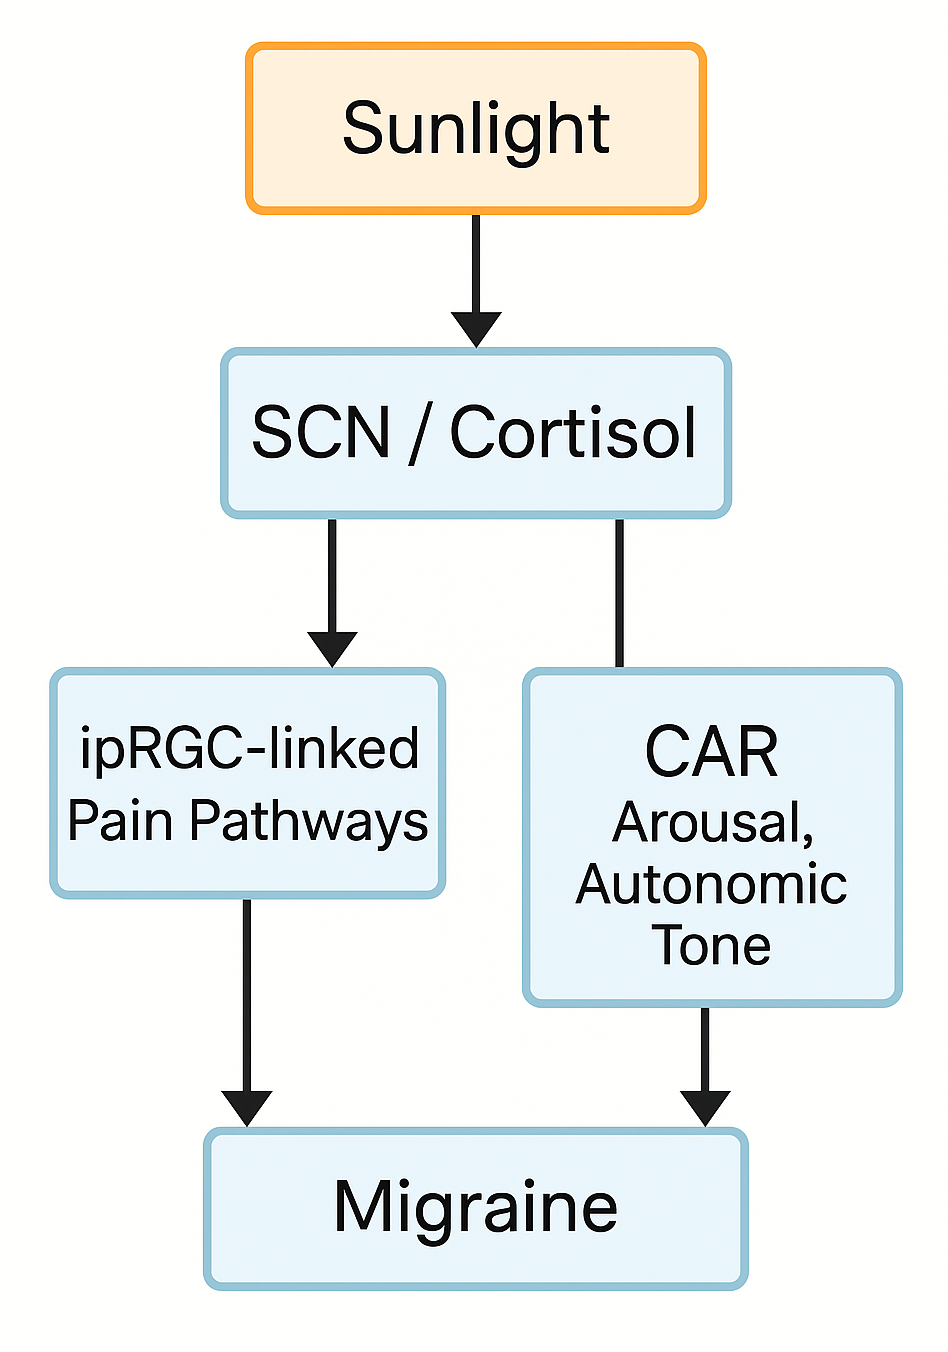
Scientific literature supports a dual pathway effect:

  1. Morning light influences the CAR – some studies show early-light exposure enhances CAR (Petrowski et al., 2019; Petrowski et al., 2022), while others reveal variability based on timing, intensity, and wavelength (Jung, 2010; Rahman et al., 2019; Leproult, Colecchia, L’Hermite-Baleriaux, & Van Cauter, 2001).
  2. Light directly triggers migraine via ipRGCs – melanopsin-containing intrinsically photosensitive retinal ganglion cells transmit light signals not only to the SCN but also to pain-processing regions (Noseda et al., 2010; McAdams et al., 2020). In migraineurs, these cells are hypersensitive to blue light; blocking their activity or using optical tints can reduce photophobia and pain (Posternack et al., 2023; Nagata et al., 2024). Experimental research confirms blue light triggers stronger pupillary and neurological responses than other wavelengths in migraine patients (Ali et al., 2021; Antemie et al., 2023).

____________

A Dual-Trigger Model

The data supports a dual-trigger model:

  • Immediate photonic activation: Intense early light activates ipRGC-driven migraine pathways.
  • Cortisol modulation: Simultaneously, light affects the CAR, either amplifying or suppressing cortisol, which may modulate susceptibility to migraine, increasing vulnerability in sensitized individuals.

This model explains why identical light exposures may be innocuous for many but debilitating for individuals with migraine sensitivity tied to cortisol and ipRGC pathways.

Evidence-Based Strategy for Prevention

Combining biological insights with lived experience suggests effective strategies:

  • Minimize direct sunrise glare – via hats, dawn-dimming curtains, or adjustable blinds.
  • Delay full bright-light exposure until later in the morning.
  • Use green-enriched lighting during early hours, as green wavelengths are less likely to trigger migraine (BrainFacts, 2019; Antemie et al., 2023).
  • Maintain consistent routines (hydration, caffeine timing, exercise) to stabilize cortisol rhythm.
  • Consider optical tints targeting ipRGC stimuli as adjunct preventive tools (Posternack et al., 2023).

Conclusion

Cortisol is a pivotal entrainer of daily energy rhythms, yet bright light, though beneficial for circadian health, can serve as a migraine trigger. In individuals with long-established patterns, sunrise light carries dual potency: energizing via cortisol rhythms and activating pain pathways via ipRGCs. By recognizing and balancing these realities, and protecting against light-triggered migraines while preserving circadian rhythm integrity, individuals can optimize energy, cognition, and long-term health.

References:

Ali, E. N., et al. (2021). Assessing migraine patients with multifocal pupillographic perimetry: pupillary abnormalities following migraine attacks. BMC Neurology, 21, Article 239. https://doi.org/10.1186/s12883-021-02239-z

Antemie, R. G., et al. (2023). Blue light—ocular and systemic damaging effects. International Journal of Molecular Sciences, 24(6), 5998. https://doi.org/10.3390/ijms24065998

Fries, E., Dettenborn, L., & Kirschbaum, C. (2009). The cortisol awakening response (CAR): Facts and future directions. International Journal of Psychophysiology, 72(1), 67–73. https://doi.org/10.1016/j.ijpsycho.2008.03.014

Franklyn-Miller, A. (2025, July 20). Expert shares the surprising role cortisol plays in our sleep—and why it’s just as important as melatonin. Tom’s Guide. Retrieved from Tom’s Guide website. https://health.yahoo.com/wellness/sleep/articles/expert-shares-surprising-role-cortisol-053000626.html

Huberman Lab. (2025, March). Using light for health [Newsletter]. Huberman Lab. Retrieved from Huberman Lab website.

Jung, C. M., Khalsa, S. B. S., Scheer, F. a. J. L., Cajochen, C., Lockley, S. W., Czeisler, C. A., & Wright, K. P. (2010). Acute effects of bright light exposure on cortisol levels. Journal of Biological Rhythms, 25(3), 208–216. https://doi.org/10.1177/0748730410368413

Leproult, R., Colecchia, E. F., L’Hermite-Balériaux, M., & Van Cauter, E. (2001). Transition from Dim to Bright Light in the Morning Induces an Immediate Elevation of Cortisol Levels1. The Journal of Clinical Endocrinology & Metabolism, 86(1), 151–157. https://doi.org/10.1210/jcem.86.1.7102

McAdams, H., et al. (2020). Selective amplification of ipRGC signals accounts for paradoxical behavioral light aversion in migraine patients. Proceedings of the National Academy of Sciences, 117(38), 23276–23283. https://doi.org/10.1073/pnas.2007402117

Noseda, R., Kainz, V., Jakubowski, M., Gooley, J. J., Saper, C. B., Digre, K., & Burstein, R. (2010). A neural mechanism for exacerbation of headache by light. Nature Neuroscience, 13(2), 239–245. https://doi.org/10.1038/nn.2475

Nagata, E., et al. (2024). Hypersensitivity of intrinsically photosensitive retinal ganglion cells in migraine. International Journal of Molecular Sciences, 25(14), 7980. https://doi.org/10.3390/ijms25147980

Petrowski, K., Schmalbach, B., Linhardt, M., Mekschrat, L., & Rohleder, N. (2022). The inflammatory immune system after wake up in healthy male individuals: A highly standardized and controlled study. Brain Behavior & Immunity – Health, 25, 100504. https://doi.org/10.1016/j.bbih.2022.100504

Petrowski, K., Schmalbach, B., Niedling, M., & Stalder, T. (2019). The effects of post-awakening light exposure on the cortisol awakening response in healthy male individuals. Psychoneuroendocrinology, 108, 28–34. https://doi.org/10.1016/j.psyneuen.2019.05.016

Posternack, C., Kupchak, P., Capriolo, A. I., & Katz, B. J. (2023). Targeting the intrinsically photosensitive retinal ganglion cell to reduce headache pain and light sensitivity in migraine: A randomized double-blind trial. Journal of Clinical Neuroscience, 113, 22–31. https://doi.org/10.1016/j.jocn.2023.04.015

Rahman, S. A., Wright, K. P., Lockley, S. W., Czeisler, C. A., & Gronfier, C. (2019). Characterizing the temporal Dynamics of Melatonin and Cortisol Changes in Response to Nocturnal Light Exposure. Scientific Reports, 9(1). https://doi.org/10.1038/s41598-019-54806-7

Rüger, M., Gordijn, M. C. M., Beersma, D. G. M., de Vries, B., & Daan, S. (2006). Time-of-day-dependent effects of bright light exposure on human cortisol responses. American Journal of Physiology-Regulatory, Integrative and Comparative Physiology, 290(1), R141–R147. https://doi.org/10.1152/ajpregu.00121.2005

About the Instructor, Author & Artist – Jim Moltzan

My journey into health, fitness, and martial arts began at the age of 16. At the time, I could not have imagined that something I started as a teenager would continue to shape nearly every stage of my adult life. What began primarily as physical training gradually developed into a much broader study of the relationship between body, mind, health, and personal development. Nearly 45 years later, I am still training, still teaching, and perhaps most importantly, still learning.

Martial arts provided the foundation. My early years were rooted in Korean martial arts, eventually expanding into practices such as BaguaZhang, tai chi, qigong, and other Eastern mind-body disciplines. Over the years I trained with a wide variety of teachers, earned a 5th-degree black belt in Korean Kung Fu through the Dong Han lineage, and accumulated well beyond 10,000 hours as a student and instructor. Yet some of the most valuable lessons came from discovering that rank, titles, forms, and years of training do not necessarily equal wisdom. They represent experience, but what we do with that experience matters much more.

My path was never particularly direct. I continued training while attending school, working multiple jobs, raising a family, and building businesses. I eventually moved from the Midwest to Florida in pursuit of a long-held goal of owning a martial arts school and ultimately became an owner of two martial arts and wellness schools. In time, however, I discovered that owning a school and being a teacher were not necessarily the same thing. Running a business could consume much of the time and energy that originally drew me to the work. I eventually chose to place greater emphasis on teaching, personal cultivation, writing, and sharing what I had learned.

That transition also changed the way I thought about health. Decades of martial arts had already introduced me to qigong, Traditional Chinese Medicine, meditation, breathing practices, and Eastern philosophy, but I wanted to understand these ideas from perspectives outside the traditions in which I had originally encountered them. In my late 50s, I returned to college and completed a Bachelor of Science degree in Holistic Health. The experience exposed me to a much broader academic examination of human health, behavior, stress, nutrition, psychology, physiology, culture, and different approaches to medicine. More importantly, it encouraged me to compare what I had learned through decades of experience with modern research and other ways of understanding health.

Teaching has remained the common thread connecting all of these experiences. I have had the opportunity to work with hundreds of people, from younger martial artists to older adults and individuals facing chronic health challenges. My teaching has taken me into martial arts schools, hospitals, wellness programs, churches, and community organizations. As I have grown older myself, my interests have naturally evolved. I remain interested in what the human body can accomplish, but I am equally interested in how we preserve movement, balance, confidence, independence, curiosity, and purpose throughout life.

Writing has become another way of teaching. Books, articles, educational materials, and hundreds of videos allow me to share what I have learned with people I may never have the opportunity to meet personally. My goal is not to present myself as a guru or someone who possesses all the answers. After theses many years, I probably have more questions than I once did. Experience has taught me to respect traditional knowledge without assuming that everything old is true, and to respect modern knowledge without assuming that everything new is necessarily better.

Perhaps the greatest change has been in how I now define health itself. I once approached health largely through training and physical capability. Today, I see it as something far more interconnected. How we move and eat certainly matters, but so do the people around us, the way we think, our ability to adapt, our sense of purpose, and whether we continue to participate meaningfully in our own lives. Good health has always required an investment of some kind, whether through time, effort, resources, sacrifice, or a combination of them. No teacher, physician, healer, or health system can make that investment entirely on our behalf.

Now, as a husband, father of two grown children, teacher, author, and lifelong student entering my own later years, I find myself less interested in accumulating and more interested in integrating. I want to make better use of what I have already learned, continue questioning what I think I know, and share whatever may be useful to others. If nearly 45 years of training and teaching have taught me anything, it is that there probably is no final destination called mastery. There is simply another opportunity to learn, adapt, help someone else, and become a little better version of ourselves along the way.

Be Well.


Jim Moltzan

www.MindAndBodyExercises.com

https://www.facebook.com/MindAndBodyExercises

https://www.youtube.com/c/MindandBodyExercises

https://mindandbodyexercises.wordpress.com

https://www.amazon.com/author/jimmoltzan

https://substack.com/@mindandbodyexercises

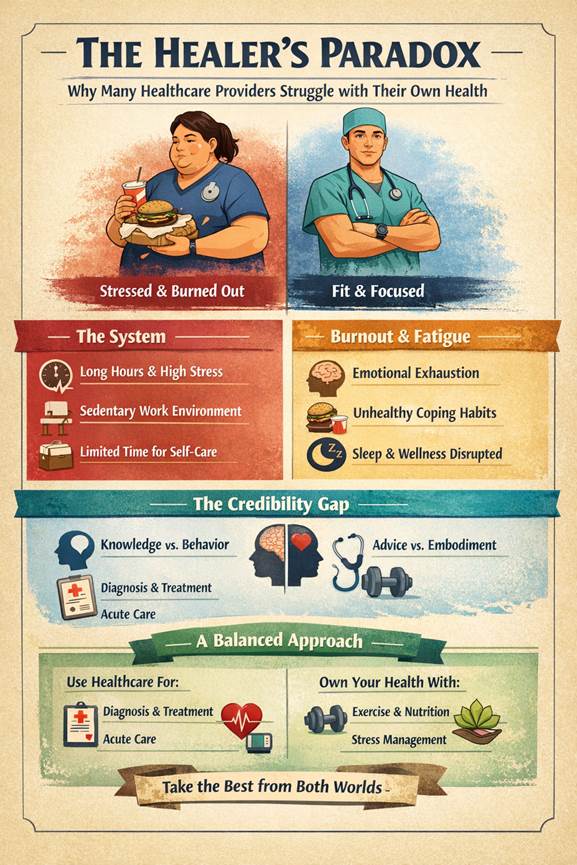
The Healer’s Paradox: When Healthcare Providers Struggle with Their Own Health

A Holistic Reflection on Credibility, Burnout, and the Modern Medical System

It is not uncommon for individuals committed to a disciplined lifestyle, regular movement, mindful nutrition, and stress management to encounter a perplexing contradiction within the modern healthcare system. Many patients report a growing sense of frustration when the very professionals advising them on weight management, exercise, and lifestyle modification appear to be struggling with those same issues themselves.

This observation raises an important question:

How should one reconcile medical advice when the messenger does not appear to embody the message?

This is not merely a personal frustration; it reflects a deeper paradox within contemporary healthcare.

The Knowledge–Behavior Gap

Healthcare professionals are extensively trained in anatomy, physiology, pathology, and disease management. They understand, often better than most, the importance of:

  • Regular physical activity
  • Nutrient-dense diets
  • Sleep hygiene
  • Stress regulation

Yet research consistently shows that knowledge alone does not guarantee behavior change. This phenomenon is often referred to as the knowledge–behavior gap and is well documented in behavioral science (Kwasnicka et al., 2016).

Even highly educated individuals are subject to:

  • Decision fatigue
  • Self-regulation depletion
  • Emotional exhaustion

In other words, knowing what to do and having the capacity to consistently do it are two very different things.

An Unhealthy System Producing Unhealthy Outcomes

A critical factor often overlooked is the structure of the healthcare system itself.

Healthcare professionals frequently work under conditions that are inherently misaligned with health:

  • Long shifts (often exceeding 10–12 hours)
  • Irregular schedules and sleep disruption
  • High patient volumes
  • Administrative overload
  • Continuous exposure to illness, trauma, and mortality

These conditions create a physiological environment characterized by chronic stress activation. Elevated cortisol levels, disrupted circadian rhythms, and prolonged sedentary behavior all contribute to metabolic dysfunction, weight gain, and declining overall health (Melamed et al., 2006; Shanafelt et al., 2015).

Thus, the issue is not simply individual failure, it is systemic.

Burnout: The Silent Epidemic Among Healthcare Workers

Burnout has become one of the most significant occupational hazards in healthcare. It is defined by:

  • Emotional exhaustion
  • Depersonalization
  • Reduced sense of personal accomplishment

Studies suggest that a substantial proportion of physicians and healthcare workers experience burnout at some point in their careers (Shanafelt et al., 2015).

From a physiological and behavioral perspective, burnout leads to:

  • Reduced motivation for self-care
  • Increased reliance on convenience foods
  • Decreased physical activity
  • Impaired emotional regulation

What may appear externally as neglect or hypocrisy is often the visible manifestation of internal depletion.

Why Do Some Providers Appear Healthier Than Others?

Interestingly, many individuals observe that certain specialists, particularly surgeons, often appear to maintain better physical condition.

Several factors may contribute:

  • Selection bias: Surgical fields tend to attract highly disciplined, performance-oriented individuals
  • Cultural expectations: Physical stamina and endurance are often emphasized
  • Financial resources: Greater access to high-quality food, fitness facilities, and time-saving services
  • Career autonomy: Increased control over scheduling later in practice

However, it is important to note that even within these groups, burnout and stress-related disorders remain prevalent.

The Credibility Dilemma

From a holistic perspective, credibility is not derived solely from knowledge, it is also rooted in embodiment.

When a healthcare provider advises:

  • “Lose weight”
  • “Exercise more”
  • “Reduce stress”

…yet appears to struggle with those same challenges, it can create a disconnect that undermines trust.

This tension highlights an important distinction:

Clinical Expertise vs. Personal Practice

A provider may possess:

  • High-level diagnostic and medical knowledge

…while simultaneously lacking:

  • Consistent personal health practices

These are not mutually inclusive domains.

A Clash of Health Paradigms

At a deeper level, this issue reflects a broader divide between two models of health:

Conventional Medical Model

  • Disease management
  • Symptom control
  • Pharmaceutical intervention
  • Reactive care

Holistic Model

  • Prevention and self-regulation
  • Mind–body integration
  • Lifestyle as medicine
  • Personal responsibility

For individuals grounded in holistic disciplines such as yoga, tai chi, qigong, and mindful living, this divergence can feel particularly stark.

A Practical and Balanced Approach

Rather than rejecting conventional medicine outright, or accepting it without question, a more refined approach is warranted.

Utilize the Healthcare System For:

  • Diagnostic testing and screening
  • Acute and emergency care
  • Risk assessment and monitoring

Cultivate Personal Responsibility For:

  • Daily movement and exercise
  • Nutritional choices
  • Stress management practices
  • Sleep and recovery

Seek Alignment When Possible

There is a growing field of practitioners who bridge both worlds:

  • Lifestyle medicine physicians
  • Integrative and functional medicine providers
  • Practitioners who embody the principles they teach

Final Reflection

The apparent contradiction within healthcare providers is not simply hypocrisy. It is a reflection of:

  • Human limitations
  • Chronic systemic stress
  • A disconnect between knowledge and lived experience

For the discerning individual, the path forward is not one of rejection, but of discernment.

Take what is useful. Question what is not. And remain rooted in practices that cultivate true health from within.

In doing so, one becomes not merely a patient within a system—but an active participant in their own well-being.

References

Kwasnicka, D., Dombrowski, S. U., White, M., & Sniehotta, F. (2016). Theoretical explanations for maintenance of behaviour change: A systematic review of behaviour theories. Health Psychology Review, 10(3), 277–296. https://doi.org/10.1080/17437199.2016.1151372

Melamed, S., Shirom, A., Toker, S., Berliner, S., & Shapira, I. (2006). Burnout and risk of cardiovascular disease: Evidence, possible causal paths, and promising research directions. Psychological Bulletin, 132(3), 327–353. https://doi.org/10.1037/0033-2909.132.3.327

Shanafelt, T. D., Hasan, O., Dyrbye, L. N., Sinsky, C., Satele, D., Sloan, J., & West, C. P. (2015). Changes in burnout and satisfaction with work-life balance in physicians and the general US working population between 2011 and 2014. Mayo Clinic Proceedings, 90(12), 1600–1613. https://doi.org/10.1016/j.mayocp.2015.08.023